How Is POTS Diagnosed? Tests, Timelines, and What to Expect
23:15
If you've been searching for answers about your racing heart, dizziness, and fatigue, you're probably wondering: how do doctors actually diagnose POTS? The short answer is that Postural Orthostatic Tachycardia Syndrome is diagnosed when your heart rate increases by 30 beats per minute or more (40 bpm for adolescents) within 10 minutes of standing, without a significant drop in blood pressure. But the reality of getting that diagnosis is far more complicated than a single test.
For most people with POTS, the path to diagnosis is long, frustrating, and often emotionally exhausting. A significant gender disparity exists in POTS diagnosis: women wait an average of 5.0 years compared with 3.0 years for men, a difference that persists after controlling for other factors. Many are told their symptoms are "just anxiety" before anyone thinks to check their heart rate while standing.
This guide walks you through everything you need to know about the POTS diagnostic process, from the official criteria to what the tests actually feel like, and what to do if doctors aren't taking your symptoms seriously.
Before diving into the tests themselves, it's important to understand why so many people struggle to get diagnosed. The statistics paint a troubling picture.
The Numbers Behind the Diagnostic Delay
The largest survey of POTS patients to date — nearly 5,000 respondents — found a mean delay of 4.9 years between initial presentation to a physician and diagnosis, with a median of 24 months. An Australian POTS registry study reports similar figures, with many patients waiting six years or more.
During this time, patients see seven physicians on average before someone finally identifies POTS. About one in five consult more than 10 doctors before getting answers, and 34% ultimately suggest the diagnosis to their doctor themselves.
There is a significant gender disparity in POTS diagnosis. Women wait an average of 5 years for diagnosis compared to 3 years for men. Given that 80-85% of POTS patients are female, this disparity affects the vast majority of people with the condition.
Clinicians have publicly acknowledged that dismissiveness — and in some cases gender bias — contributes to the diagnostic delay women with POTS experience.
The irony is that POTS isn't difficult to diagnose once a physician knows what to look for. The diagnostic tests are simple, inexpensive, and can be done in any doctor's office.
POTS Diagnosis Research
Understanding the POTS Diagnostic Journey
The Long Road to Diagnosis
What POTS patients experience before getting answers
4.9YearsAverage Diagnostic DelayShaw et al., 2019 (n=4,835)
7DoctorsSeen Before DiagnosisMedian: 5, IQR: 3-8
34%Self-DiagnosedSuggested Diagnosis ThemselvesDysautonomia International
The Misdiagnosis Problem
How often POTS patients are told it's psychological Source: Shaw et al., J Intern Med, 2019
Told symptoms were psychological or psychiatric77%
Doctor acknowledged illness but didn't know how to proceed67%
Being treated for a psychiatric condition before POTS diagnosis28%
Saw 10+ doctors before diagnosis21%
"Research shows POTS patients have no increased prevalence of anxiety disorders compared to the general population." — Raj et al.
The Gender Gap in Diagnosis
Women wait significantly longer for a POTS diagnosis
👨Men3years to diagnosis
VS
👩Women5years to diagnosis
POTS Diagnostic Criteria
Heart rate increase within 10 minutes of standing
Adults (Age 20+)≥30BPM increase
Or heart rate exceeding 120 BPM within 10 minutes of standing
Adolescents (Age 12-19)≥40BPM increase
Higher threshold due to normal adolescent heart rate variability
Important: Diagnosis requires ruling out orthostatic hypotension (blood pressure drop ≥20/10 mmHg) and symptoms present for at 6+ months.
Source: Sheldon et al., Heart Rhythm, 2015; Vernino et al., Auton Neurosci, 2021
The COVID-19 POTS Surge
New POTS diagnoses before vs. after the pandemic
Pre-COVID (2012-2019)4.21new cases per month
5x increase
Post-COVID (2020-2024)22.66new cases per month
Source: Blitshteyn et al., Eur Heart J Qual Care Clin Outcomes, 2025
POTS Rarely Travels Alone
Common conditions that occur alongside POTS
Up to 80% EDS Patients have POTS (varies by diagnostic method)
— Miller et al., Auton Neurosci, 2020
r
Roughly half experience Small Fiber Nerve Involvement (diagnosed via QSART or skin biopsy)
— Gibbons et al., PLOS One, 2014
Meaningful subset experience MCAS Overlap
— Shibao et al., Hypertension, 2005
Note: At Cognitive FX, we treat POTS as a neurological condition rather than a cardiovascular one — targeting the autonomic nervous system and brainstem centers that miscalibrate heart rate and blood pressure signals in the first place. Our five-day program combines neuro-cardio training, vestibular recalibration, breathing mechanics, and CO₂-based therapies to retrain the systems driving symptoms. If POTS is disrupting your daily life, schedule a free consultation to see whether our approach is a fit for you.
The Official Diagnostic Criteria for POTS
Understanding the diagnostic criteria can help you advocate for proper testing. Here's what medical professionals look for.
For adolescents between ages 12 and 19, the threshold is higher: a heart rate increase of 40 bpm or more within 10 minutes of standing. This higher threshold exists because healthy teenagers naturally experience more heart rate variability when changing positions.
What Must Be Ruled Out
A POTS diagnosis requires ruling out orthostatic hypotension, which is a significant drop in blood pressure upon standing (20 mmHg systolic or 10 mmHg diastolic within 3 minutes). If blood pressure drops substantially when you stand, that's a different condition that requires different treatment.
Symptoms must be present for at least 6 months to be considered chronic. This helps distinguish POTS from temporary conditions like dehydration or acute illness that can cause similar symptoms short-term.
Common Symptoms That Prompt Testing
While the diagnostic criteria focus on heart rate, doctors should consider POTS testing when patients report a wider constellation of symptoms like lightheadedness or dizziness when standing, heart palpitations or racing heart, fatigue that worsens with activity, brain fog or difficulty concentrating, exercise intolerance, nausea, headaches, shakiness or tremors, and chest discomfort. Symptoms characteristically improve when lying down and worsen when upright.
The Tilt Table Test: What Actually Happens
The tilt table test is considered the gold standard for POTS diagnosis. Here's what to expect if your doctor orders one.
Before the Test
You'll need to fast for 2 to 4 hours before the test, meaning no food or drinks. Avoid caffeine entirely on test day. Your doctor may ask you to temporarily stop certain medications that could affect the results, including beta-blockers, calcium channel blockers, and some antidepressants. Always discuss medication changes with your prescribing physician first.
Plan to have someone drive you home afterward, as you may feel tired or lightheaded.
During the Test
The test takes place in a cardiology or autonomic testing lab. Here's the typical sequence.
You'll lie flat on a special motorized table with a footrest and safety straps around your torso and legs. Medical staff will attach ECG electrodes to monitor your heart rhythm, a blood pressure cuff on your arm (and sometimes a continuous finger blood pressure monitor), and a pulse oximeter on your finger.
You'll rest in the flat position for 5 to 20 minutes while baseline measurements are recorded. Then the table tilts to an angle between 60 and 80 degrees (most commonly 70 degrees) over about 15 seconds. You'll remain in this near-upright position, supported by the footrest and straps, for 10 to 45 minutes.
Throughout the test, staff continuously monitor your heart rate, blood pressure, and symptoms. You'll be asked to stay as still as possible and avoid tensing your leg or buttock muscles, as this can affect results.
What It Feels Like
Most people with POTS will start experiencing their typical symptoms during the tilt portion: racing heart, dizziness, lightheadedness, sweating, nausea, or that familiar "I need to sit down" feeling. Some patients faint during the test, which is actually useful diagnostic information. If this happens, the table is immediately returned to horizontal.
The test isn't painful, but it can be uncomfortable, especially if you're used to avoiding standing for long periods. Many patients describe it as "like standing in line at the DMV, but lying down."
After the Test
The table returns to horizontal, and you'll rest for 15 to 20 minutes while your vitals normalize. Staff may discuss preliminary results with you immediately, though formal results typically come within a few days.
Plan for the rest of the day to be low-key. Many people feel tired or "off" for several hours after the test.
Accuracy Considerations
While the tilt table test is considered the gold standard, it's not perfect. Sensitivity is around 93% at 10 minutes, meaning it catches most POTS cases, but specificity at the standard 30 bpm threshold is only about 40% — some people without POTS may test positive.
This is why diagnosis shouldn't rely solely on heart rate numbers. The presence of characteristic symptoms during the test is equally important.
Alternative Testing Options
Not everyone has access to a tilt table test, and some doctors prefer simpler in-office assessments. Here are the alternatives.
The Active Standing Test
This test can be performed in any doctor's office with basic equipment. You lie flat for 10 minutes while baseline heart rate and blood pressure are recorded. Then you stand as still as possible for 10 minutes while measurements are taken at 2, 5, and 10 minute intervals.
The key difference from the tilt table test is that active standing involves your "skeletal muscle pump," where leg muscle contractions help push blood back toward your heart. This can reduce the heart rate response compared to passive tilting.
Originally developed by NASA to study astronauts with orthostatic intolerance, this test requires minimal equipment and can even be performed at home for preliminary screening.
The protocol involves lying flat for 10 minutes to establish baseline measurements, then standing with your shoulder blades against a wall and your heels 6 to 8 inches away from the wall. You maintain this relaxed leaning position for 10 minutes while heart rate and blood pressure are measured each minute.
The wall support provides a middle ground between passive tilt table testing and active standing. It's particularly useful for patients who have difficulty standing unsupported for extended periods.
Can You Test for POTS at Home?
While a formal diagnosis requires medical evaluation, you can do a preliminary assessment at home using the active standing test or NASA lean test protocols. You'll need a reliable blood pressure monitor that also displays heart rate, or a pulse oximeter and separate blood pressure cuff.
However, there are important caveats. Home testing can provide useful information to bring to your doctor, but shouldn't replace professional evaluation. Results can vary based on time of day, hydration status, recent meals, and other factors. A single positive home test doesn't confirm POTS, and a negative test doesn't rule it out.
If your home testing suggests POTS, bring your documented measurements to your doctor as evidence to support formal testing.
Other Tests You May Need
Diagnosing POTS often involves ruling out other conditions and identifying potential underlying causes. Here are additional tests your doctor may order.
Blood Work
Standard labs help rule out conditions that can cause similar symptoms. These typically include complete blood count to check for anemia, thyroid function tests to rule out hyperthyroidism, a basic or comprehensive metabolic panel for electrolyte abnormalities, iron studies, cortisol levels for adrenal function, glucose and HbA1c for diabetes, celiac panel, ANA and inflammatory markers for autoimmune conditions, and vitamin B12.
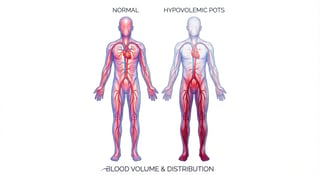
A 24-hour urine collection for catecholamines helps rule out pheochromocytoma, a rare adrenal tumor. Low urinary sodium in the collection may indicate the hypovolemic POTS subtype.
Autonomic Function Testing
A comprehensive autonomic evaluation may include the Valsalva maneuver, where you blow into a tube at a set pressure while heart rate and blood pressure are monitored. There's also heart rate variability testing during deep breathing, which assesses parasympathetic function, and the isometric handgrip test for additional autonomic assessment.
QSART Testing
The Quantitative Sudomotor Axon Reflex Test measures sweat gland function controlled by small nerve fibers. Electrodes placed on your forearm and legs deliver mild electrical stimulation while sweat output is measured. A meaningful proportion of POTS patients have abnormal results on this test, often showing reduced sweating in the legs and feet. This helps identify neuropathic POTS. This helps identify neuropathic POTS.
Cardiac Tests
An echocardiogram uses ultrasound to visualize your heart, ruling out structural abnormalities or valve problems like mitral valve prolapse. A 24-hour Holter monitor continuously records your heart rhythm, helping identify arrhythmias and documenting heart rate patterns during symptomatic episodes.
When to Test for Comorbidities
POTS rarely exists in isolation. Your doctor should consider screening for Ehlers-Danlos Syndrome (EDS) if you have joint hypermobility, stretchy skin, or easy bruising, since 80% of EDS patients have POTS. Mast Cell Activation Syndrome (MCAS) testing is warranted if you have flushing, hives, or unexplained allergic-type reactions, as 42% of POTS patients have MCAS symptoms.
Finding the right specialist can significantly impact your diagnostic journey.
Who Diagnoses POTS Most Often
Research on POTS patients shows that cardiologists diagnose 41% of cases, neurologists diagnose 19%, cardiac electrophysiologists diagnose 15%, and family physicians diagnose 8%.
Understanding Specialist Roles
Cardiologists are often the first specialists patients see because of heart-related symptoms like palpitations and racing heart. They can order tilt table tests, echocardiograms, and Holter monitors. However, not all cardiologists are familiar with POTS.
Cardiac electrophysiologists subspecialize in heart rhythm disorders and traditionally have been considered "POTS experts." They developed the tilt table test and often have the most experience with autonomic conditions. But these specialists are scarce relative to the estimated 1 to 3 million POTS patients in the US, which contributes to long wait times.
Neurologists may be particularly helpful if your symptoms include brain fog, headaches, or suspected small fiber neuropathy. They can perform QSART testing and order skin biopsies.
Autonomic specialists are the ideal choice for complex cases, but they're rare. Dedicated autonomic clinics exist at major centers like Vanderbilt, Mayo Clinic, Cleveland Clinic, and Johns Hopkins. Wait times can exceed a year.
Can Your Primary Care Doctor Diagnose POTS?
Yes. Any physician can diagnose POTS if you meet the criteria. A primary care doctor can perform an active standing test in the office, order basic blood work, and make the diagnosis if results are clear.
The challenge is finding a primary care provider who knows what POTS is and takes the symptoms seriously. If your doctor dismisses your concerns, consider seeking a second opinion or requesting a referral to a specialist.
How to Find a POTS-Knowledgeable Provider
Dysautonomia International maintains a physician directory at dysautonomiainternational.org. Standing Up to POTS at standinguptopots.org also offers resources. Local POTS support groups on Facebook or Reddit often share recommendations.
When calling to schedule, ask directly: "Does this doctor have experience diagnosing and treating POTS?"
One of the most painful aspects of the POTS diagnostic journey is encountering medical professionals who dismiss your symptoms. Here's how to advocate for yourself.
Distinguishing POTS from Anxiety
POTS and anxiety share overlapping symptoms like racing heart, sweating, and feeling faint. This is why so many POTS patients are initially misdiagnosed with anxiety disorders. But there are key differences.
With POTS, symptoms are triggered by position changes and improve when lying down. Anxiety symptoms can occur in any position and aren't reliably relieved by lying flat. POTS symptoms have measurable physiological markers, specifically the heart rate increase upon standing. Anxiety-related heart rate increases don't follow this predictable positional pattern.
As one patient put it: "A POTS episode is pretty easy to tell from anxiety. There's little to no psychological anxiety, panic, or worry. You just feel out of it and very sick. It's all physical."
Scripts for Doctor's Appointments
If you suspect POTS, try these approaches. You might say "I've noticed my heart rate increases significantly when I stand up. I've been tracking it at home. Can we do a standing test to check for POTS?" Or "I know my symptoms might look like anxiety, but they only happen when I'm upright and get better when I lie down. That pattern suggests something autonomic might be going on." Or "I'd like to try a 10-minute standing test before we attribute this to anxiety. If my heart rate increases by 30 beats per minute, that would meet the criteria for POTS."
When to Seek a Second Opinion
Consider finding a new provider if your doctor refuses to perform basic testing, if you're told it's "just anxiety" without any objective measurements, if symptoms are dismissed because "your labs are normal," or if you've been given psychiatric medication that hasn't helped and no one has reconsidered the diagnosis.
Documenting Your Symptoms
Bring evidence to appointments. Keep a symptom diary noting when symptoms occur, what triggers them, and what helps. Record home heart rate and blood pressure measurements in different positions. Track heart rate patterns using a fitness tracker or smartwatch. Note how symptoms impact your daily function, like whether you have difficulty working, exercising, or standing in line.
Patient Advocacy Guide
Questions to Ask Your Doctor About POTS
Use these evidence-based questions to help get the testing, diagnosis, or referral you need. Many patients wait years because they don't know what to ask.
34%Suggest Diagnosis Themselves
4.9Years Average Delay
7Doctors Before Diagnosis
🩺
Requesting a Standing Test
Start here if you haven't been tested for POTS
Question 1"Can we measure my heart rate and blood pressure while lying down, and then again after I've been standing for 10 minutes?"
Why it works: This describes the active standing test without medical jargon. Any doctor can do this in-office with basic equipment.
Question 2"I've noticed my heart rate increases significantly when I stand up. I've been tracking it at home. Can we verify this together?"
Why it works: Bringing documented evidence shows you've done your homework and gives the doctor concrete data to work with.
Question 3"My symptoms only happen when I'm upright and get better when I lie down. Could we test for orthostatic intolerance or POTS?"
Why it works: Emphasizing the positional pattern is key. This distinguishes your symptoms from anxiety or other conditions.
💬
If You've Been Told It's "Just Anxiety"
77% of POTS patients are told their symptoms are psychiatric before getting a POTS diagnosis (Shaw et al., 2019)
Question 4"I understand anxiety can cause similar symptoms, but mine follow a specific pattern. Can we rule out POTS before concluding it's anxiety?"
Why it works: You're not dismissing their assessment, just requesting objective testing first. A 10-minute standing test can provide clarity.
Question 5"If my heart rate increases by 30+ bpm when I stand, would that change your assessment? Can we check?"
Why it works: This gives the doctor a measurable threshold to test against. A 30+ bpm increase is the diagnostic criteria for adults.
Question 6"The anxiety medication hasn't helped my physical symptoms. Could there be an underlying autonomic issue we haven't explored?"
Why it works: If you've tried anxiety treatment without improvement, this is important diagnostic information that warrants further investigation.
📋
Requesting a Specialist Referral
Cardiologists diagnose 41% of POTS cases
Question 7"Could you refer me to a cardiologist or electrophysiologist who has experience with dysautonomia or POTS?"
Why it works: Specifying "experience with dysautonomia" helps you get a specialist who actually knows how to diagnose and treat POTS.
Question 8"I'd like a referral for a tilt table test. Which specialists in our network can perform this?"
Why it works: Directly requesting the specific test shows you know what you need. Tilt table tests are typically done by cardiologists or in autonomic labs.
Question 9"If you're not comfortable diagnosing this, who would you recommend I see for a second opinion on autonomic dysfunction?"
Why it works: This is respectful but direct. It acknowledges their expertise while opening the door to see someone more specialized.
🔍
After Testing or Diagnosis
Important follow-up questions to understand your results
Question 10"What was my heart rate increase upon standing? Does that meet the criteria for POTS?"
Why it works: Get the actual numbers. Adults need 30+ bpm increase; adolescents need 40+ bpm. You deserve to know your specific results.
Question 11"Should we test for underlying causes or related conditions like Ehlers-Danlos Syndrome or mast cell activation?"
Why it works: Up to 80% of EDS patients also have POTS (varying by method), and a meaningful subset of POTS patients show evidence of MCAS overlap. Identifying comorbidities improves treatment outcomes.
Question 12"Can you document this diagnosis in my medical record so future providers have this information?"
Why it works: Having POTS in your official medical record prevents future providers from starting the diagnostic process over again.
💡 Pro Tips for Your Appointment
📱
Bring DataShow heart rate logs from a smartwatch or blood pressure monitor. Numbers are harder to dismiss than descriptions.
📝
Write It DownBring your questions printed out. It's easy to forget in the moment, and it shows you're prepared.
👥
Bring SupportA family member or friend can advocate for you, take notes, and help you remember what was said.
🎯
Stay FocusedLead with your most concerning symptom and the positional pattern. Don't overwhelm with every symptom at once.
Toledo researchers documented the surge in diagnoses: between January 2018 and March 2020, their clinic saw an average of 4.21 new POTS cases per month. From March 2020 through June 2024, that jumped to 22.66 new cases monthly — more than a five-fold increase.
Unique Features of Post-COVID POTS
Post-COVID POTS patients often report higher rates of brain fog, internal tremors, and tinnitus compared to other POTS patients. There's significant overlap with mast cell activation syndrome and ME/CFS. Symptoms may appear during acute infection or emerge months later.
Diagnostic Criteria for Post-COVID POTS
The American Autonomic Society recommends standard POTS criteria plus orthostatic symptoms present at least 12 weeks after COVID-19 infection. The diagnostic tests are the same as for any POTS patient.
The POTS-EDS-MCAS Connection
Researchers increasingly recognize a "trifecta" of conditions that frequently occur together: POTS, Ehlers-Danlos Syndrome, and Mast Cell Activation Syndrome.
If you have POTS, your doctor should assess for joint hypermobility using the Beighton score, a 9-point system that evaluates flexibility at various joints. High scores suggest possible hypermobile EDS and may prompt genetic evaluation.
How Cognitive FX Treats POTS
Getting a diagnosis is the first hurdle. Getting effective treatment is often the second. Most POTS care focuses on the heart and blood vessels — beta-blockers to slow the racing heart, salt and fluids to expand blood volume, compression garments to prevent pooling. These strategies help many patients function day to day. But they compensate for the dysfunction rather than fixing it, which is why symptoms return the moment the support stops.
At Cognitive FX, we treat POTS as a neurological condition. The autonomic nervous system and brainstem centers that miscalibrate heart rate and blood pressure signals are the source of the problem — the cardiovascular symptoms are downstream. We're recalibrating the thermostat, not just adjusting to a room that's always too hot.
Our POTS program grew out of years of treating brain injury patients who also had POTS symptoms. As we saw their autonomic function consistently improve through neurological rehabilitation, we refined and formalized those methods into a dedicated five-day program.
What treatment looks like
The program runs Monday through Friday, four to six hours per day. Day one is a comprehensive evaluation covering orthostatic response, vestibular function, cranial nerve inputs, and breathing mechanics. Days two through five deliver the treatment itself:
Neuro-cardio training — brief intervals through all heart rate zones with precise recovery periods, retraining the sympathetic ("gas pedal") and parasympathetic ("brake pedal") systems to work together again
Vestibular recalibration — targeting the saccule, the inner ear structure that detects vertical position changes, to reduce the orthostatic overreaction
Breathing mechanics training — restoring nasal and diaphragmatic breathing patterns and addressing the low CO₂ levels common in POTS
Cranial nerve activation — targeted smell and taste inputs (lavender and vanilla activate parasympathetic; citrus and peppermint activate sympathetic) to influence the brainstem centers regulating heart rate and breathing
CO₂-based therapies — pre-cardio inhalation to improve oxygen delivery, and a CO₂ recovery suit during rest phases for tissue perfusion
Rest and recovery blocks are built into every day to protect patient tolerance. Patients leave with a home program tailored to their specific dysregulation pattern.
Who this is for
The program is designed for patients who have a confirmed POTS diagnosis — or strongly suspect they have POTS — and who haven't gotten lasting improvement from standard cardiovascular-focused treatment. The full cost is $4,500, which includes the evaluation, all treatment sessions, and follow-up consultations. Insurance doesn't currently cover the program directly, though we provide documentation and billing codes for patients who want to pursue out-of-network reimbursement.
Treatment happens at our clinic in Provo, Utah. Most patients travel in from out of state or internationally, and we partner with a nearby hotel that offers patient rates and shuttle service to and from the clinic.
If you've been managing POTS for months or years and standard treatment hasn't given you your function back, the neurological approach at Cognitive FX may address what prior care has missed. Fill out the POTS intake form or call 385-446-4158 to find out whether you're a good candidate.
Frequently Asked Questions
Can POTS be diagnosed at home?
You can perform preliminary testing at home using the active standing test or NASA lean test protocols, or take a self-assessment quiz to organize your symptoms before an appointment, which may provide useful information to share with your doctor.
However, a formal POTS diagnosis requires evaluation by a healthcare provider to rule out other conditions and confirm the findings. Home testing is best used as a screening tool or to document your symptoms for medical appointments.
How long does it take to get diagnosed with POTS?
Research shows the average POTS patient waits 4 to 6 years and sees seven different doctors before receiving a diagnosis. This delay is largely due to lack of physician awareness about the condition. Patients who educate themselves about POTS and advocate for testing often receive faster diagnoses. About 34% of patients suggest the diagnosis to their doctor themselves.
Can you have POTS without fainting?
Yes. While some POTS patients do faint, many never lose consciousness. The hallmark of POTS is the heart rate increase upon standing, not fainting. Common symptoms without fainting include dizziness, lightheadedness, palpitations, fatigue, brain fog, and the feeling that you might faint even if you don't actually pass out.
What's the difference between POTS and anxiety?
POTS and anxiety can cause similar symptoms like racing heart and sweating, which is why misdiagnosis is common. The key difference is that POTS symptoms are triggered by standing upright and improve when lying down. This positional pattern doesn't occur with anxiety. Additionally, POTS produces a measurable heart rate increase of 30+ bpm upon standing, which can be objectively documented.
Is a tilt table test the only way to diagnose POTS?
No. While the tilt table test is considered the gold standard, POTS can also be diagnosed using the active standing test or NASA lean test. These simpler tests can be performed in a regular doctor's office without specialized equipment. The key requirement is measuring heart rate and blood pressure while lying down and again after standing for up to 10 minutes.
What type of doctor is best for diagnosing POTS?
Cardiologists and cardiac electrophysiologists diagnose the majority of POTS cases. Neurologists with autonomic expertise are also good options, especially if you have symptoms like brain fog or suspected neuropathy. However, any knowledgeable physician, including primary care doctors, can diagnose POTS. The most important factor is finding a provider who takes your symptoms seriously and knows how to test for the condition.
Taking the Next Step
Getting a POTS diagnosis can feel like an uphill battle, but understanding the process puts you in a better position to advocate for yourself. If you suspect you have POTS, start by tracking your symptoms and heart rate patterns at home. Bring this documentation to your doctor and specifically request testing for POTS.
Remember: You're not imagining your symptoms, and you deserve a thorough evaluation. The average diagnostic delay of nearly 5 years isn't acceptable, and you don't have to accept being dismissed.
If you've been diagnosed with POTS — or strongly suspect you have it — and standard cardiovascular-focused treatment hasn't given you your life back, Cognitive FX's five-day neurological POTS program may be worth exploring. Our approach targets the autonomic dysfunction driving symptoms, not just the heart rate response. Fill out our POTS intake form or call 385-446-4158 to speak with our patient care coordinator about whether treatment is right for you.
Dr. Lynn Gaufin graduated from the University of Utah and then attended medical school at Cornell University in New York City. After medical school he join the Army and was a surgeon in the military before finishing his Neurological Residency at University of California Los Angeles. Dr. Gaufin specializes in cervical and lumbar spine surgery, brain tumors, brain hemorrhages, and treatment of traumatic brain injuries. Dr. Gaufin is one of the emergency trauma neurosurgeons on call at Utah Valley Hospital. Before he began his practice in Utah he saw a significant amount of traumatic brain injuries during his career in the Army and his residency in Los Angeles. As a surgeon who treats individuals who suffer from mild to severe traumatic brain injuries he recognized a problem in the post operative rehabilitation. Individuals who suffered severe trauma would be admitted into speciality facilities where they would receive months of care. But patients who had a more mild trauma would be released and would largely be on their own when it came to restoring their cognitive function. That problem is what lead Dr. Gaufin to team up with Dr. Fong and Dr. Allen in the creation of Cognitive FX. Cognitive FX was able to take the research that Dr. Fong and Dr. Allen started in their Phd programs and bring it into the clinical environment.
Related Posts
POTS-Related Orthostatic Headaches: Causes and Treatment
If you have POTS, you may know the pattern all too well: you stand up, and within seconds, a headache sets in. It eases off when you lie back down. It returns the next time you stand. Over and over,...
If you’re experiencing symptoms like dizziness, lightheadedness, fainting, or a racing heart when you stand, your healthcare provider may suspect a form of dysautonomia—including postural orthostatic...
Hyperadrenergic POTS affects an estimated 30 to 60% of all POTS patients, yet most are never told which subtype they have. That matters because the hyperadrenergic form requires a fundamentally...
For patients with postural orthostatic tachycardia syndrome (POTS), proper hydration is a key part of symptom management. Many POTS patients are advised to increase their daily fluid intake, usually...
If you’re experiencing symptoms such as dizziness, rapid heartbeat, or fatigue when standing, your healthcare provider may recommend autonomic testing to evaluate for Postural Orthostatic Tachycardia...