Is There a Cure for POTS? What Patients Need to Know

If you’re living with POTS, you’ve probably wondered: Is this ever going to get better?



If you've ever stood up and felt your heart start racing, felt lightheaded out of nowhere, or experienced brain fog so thick you couldn't finish a sentence, you might be dealing with something called POTS. And if doctors have told you it's 'just anxiety' or that your tests look normal, you're definitely not alone.
Postural orthostatic tachycardia syndrome is estimated to affect between one and three million Americans, and the average patient waits years for a diagnosis, often seeing multiple physicians before anyone identifies what's happening. That's a long time to feel like something is wrong while being told nothing is.
POTS isn't just a heart problem. It's fundamentally a problem with how your brain regulates your cardiovascular system. Understanding that connection changes everything about how the condition can be treated.
In this guide, we’ll cover:
Note: Cognitive FX runs a 5-day intensive POTS program that treats the autonomic nervous system directly rather than managing symptoms alone. Patients often see improvements that standard care hasn't been able to achieve. Learn more or see if you're a good fit here, or call 385-446-4158 to speak with our team.
POTS stands for Postural Orthostatic Tachycardia Syndrome. Let's break that down:
Postural means it relates to your body position. Orthostatic means it happens when you're upright. Tachycardia means a fast heart rate. Syndrome means it's a collection of symptoms rather than a single disease.
Research reveals what's really happening in the central nervous system
Tap each region to learn more
The right insula controls sympathetic (fight-or-flight) activity, while the left insula controls parasympathetic (rest-and-digest) activity. A 2015 study found POTS patients have reduced gray matter volume in the left anterior insula, which may explain why the parasympathetic system fails to properly counterbalance sympathetic overdrive.
The paraventricular nucleus within the hypothalamus is the only brain structure in a complete feedback loop with both branches of the autonomic nervous system. When this region malfunctions, the entire system loses its ability to properly regulate heart rate, blood pressure, and other automatic functions.
The nucleus tractus solitarius and ventrolateral medulla directly control the baroreceptor reflex, the mechanism that should automatically adjust your heart rate and blood pressure when you stand. MR spectroscopy studies have found markers of neuroinflammation in the brainstem of POTS patients.
This is why standard treatments often aren't enough. Compression and salt help with blood pooling, while medications manage heart rate. But neither directly addresses dysfunction in the central autonomic network.
In practical terms, POTS is diagnosed when your heart rate increases by 30 beats per minute or more (40 bpm for adolescents) within 10 minutes of standing up, without a significant drop in blood pressure. The normal brief adjustment everyone experiences when standing is different from this sustained, exaggerated response that causes real symptoms.
When you stand up from lying down, gravity pulls roughly half a liter of blood downward into your legs and abdomen. In a healthy body, your autonomic nervous system immediately compensates by tightening blood vessels and slightly increasing heart rate to keep blood flowing to your brain and vital organs. You don't even think about it. It just happens.
In POTS, that compensation fails. Blood pools in the lower body, your stroke volume drops, and your heart races persistently to try to maintain adequate circulation. But the problem isn't really with your heart. The problem is with the system that's supposed to be controlling it.
Most people think of POTS as a cardiovascular condition. Cardiologists manage it, and the diagnostic test measures heart rate. Also, the symptoms involve the heart racing, so it makes sense that people would focus there.
However, research is increasingly showing that the root of POTS lies in dysfunction of the autonomic nervous system, which is controlled by specific regions of your brain.When those brain regions aren't functioning properly, the downstream effects show up in your heart rate, blood pressure, digestion, temperature regulation, and dozens of other "automatic" functions.
Your autonomic nervous system (ANS) isn't just a bunch of nerves running to your organs. It has a command center in your brain called the Central Autonomic Network (CAN). The central autonomic network — first mapped decades ago and refined since — includes:
Cortical regions like the insular cortex, anterior cingulate cortex, and medial prefrontal cortex. These areas integrate sensory information and help regulate emotional and physiological responses.
Subcortical structures including the hypothalamus, amygdala, and thalamus. The hypothalamus serves as the central coordinator for both branches of the autonomic nervous system.
Brainstem centers such as the nucleus tractus solitarius and the ventrolateral medulla. These regions directly control moment-to-moment cardiovascular regulation, including the baroreceptor reflex that should kick in when you stand up.
When any part of this network is disrupted, whether from injury, inflammation, infection, or other causes, the result can be autonomic dysfunction. And one of the most common manifestations of autonomic dysfunction is POTS.
A growing body of neuroimaging research confirms that POTS patients have measurable differences in brain structure and function compared to healthy controls.
MRI research has found reduced gray matter volume in the left anterior insula, right middle frontal gyrus, and right cingulate gyrus in POTS patients, precisely the regions involved in autonomic control. The volume of the left insula correlated with anxiety and depression symptoms, suggesting the structural differences contribute to multiple aspects of the condition.
Brain SPECT imaging of POTS patients with cognitive dysfunction found 61% had reduced cerebral blood flow even while lying flat, not just when standing. Their brains were chronically underperfused. The regions most affected were the prefrontal and sensorimotor cortices, and the severity of hypoperfusion correlated with worse quality of life scores. This finding is specific to POTS patients experiencing cognitive symptoms, not the entire POTS population.
Related research has documented elevated inflammatory markers in the dorsal medulla — the brainstem region controlling autonomic function — along with abnormal cerebral blood flow patterns during upright posture. The evidence increasingly points to POTS as a disorder involving the brain, not just the peripheral nervous system.
If POTS were purely a problem with blood vessels in the legs or blood volume in the body, then compression stockings and extra salt would fix everyone. These measures help some patients, but they don't help everyone, and they rarely provide complete relief. That's because they're addressing downstream effects rather than upstream causes.
When the brain regions controlling autonomic function aren't working properly, treating the symptoms alone is like putting a bucket under a leaky roof. It catches some of the water, but it doesn't fix the leak.
This is why we've seen patients at our clinic who have tried everything (salt loading, compression garments, multiple medications, exercise protocols) but still struggle with symptoms. When we assess their brain function using advanced imaging, we often find patterns of dysfunction that explain why those approaches weren't enough. And when treatment targets that brain dysfunction directly, many patients finally start to improve.
POTS isn't a single condition. It's more like an umbrella term covering several different underlying mechanisms. Understanding which type you have is crucial because the treatment approach differs for each one. Many patients actually have overlapping types, which adds to the complexity.
Tap each card to see details
Damaged nerves in the legs fail to constrict blood vessels, causing excessive blood pooling
Bluish-purple discoloration of feet when standing (acrocyanosis)
Compression garments, midodrine, pyridostigmine
Sympathetic nervous system stuck in "fight or flight" with elevated norepinephrine (≥600 pg/mL)
Tremor, excessive sweating, anxiety, feeling "wired," blood pressure rises when standing
Beta-blockers, ivabradine, clonidine to calm sympathetic activity
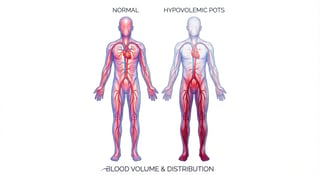
Blood volume averages 13% below normal, with paradoxically low renin and aldosterone
Symptoms worse with dehydration, often feels better after IV fluids
8-10g salt daily, 2-3L fluids, fludrocortisone
89% have elevated anti-adrenergic receptor antibodies that impair blood vessel constriction
Often triggered by viral illness; may have other autoimmune conditions or family history
Standard therapies plus immunomodulation (IVIG) in severe cases
These subtypes frequently overlap. For example, you might have both hyperadrenergic and hypovolemic features. This is why comprehensive evaluation and personalized treatment plans are essential.
Neuropathic POTS is the most common subtype, thought to affect roughly half of POTS patients. In neuropathic POTS, small nerve fibers that control blood vessel constriction are damaged, particularly in the legs. When you stand, the blood vessels don't tighten the way they should, so blood pools excessively in your lower body.
Patients with neuropathic POTS often notice a bluish-purple discoloration of their feet and lower legs when standing (called dependent acrocyanosis). They may also have patchy sweating abnormalities because the same small fibers that control blood vessels also control sweat glands.
The nerve damage can result from autoimmune processes, diabetes, or other conditions. In many cases, the exact cause is never identified. A test called QSART (Quantitative Sudomotor Axon Reflex Test) can help identify small fiber neuropathy.
Treatment for neuropathic POTS typically emphasizes compression garments (especially abdominal compression, which is often more effective than leg compression alone), medications that help constrict blood vessels like midodrine, and sometimes pyridostigmine to enhance parasympathetic activity.
A hyperadrenergic component is thought to be present in a substantial minority of POTS patients, whose sympathetic nervous system is in overdrive. These patients have elevated standing norepinephrine levels (typically above 600 pg/mL) and often experience a rise in blood pressure along with the tachycardia.
Symptoms of hyperadrenergic POTS often include prominent tremor, excessive sweating, anxiety, and a feeling of being "wired" or on edge. Some patients describe it as feeling like they're constantly in fight-or-flight mode, which is essentially accurate. Their sympathetic nervous system is stuck in the "on" position.
This type of POTS responds best to treatments that calm the sympathetic nervous system rather than those that increase blood pressure (which could make things worse). Beta-blockers, ivabradine, and central alpha-2 agonists like clonidine can help reduce the excessive sympathetic activation.
A large share of POTS patients have lower than normal blood volume, averaging about 13% below normal. Drinking more fluids alone isn't enough.
These patients often have paradoxically low levels of renin and aldosterone, the hormones that should increase when blood volume is low. At the same time, their angiotensin II levels are elevated, suggesting their bodies are trying to compensate but the normal regulatory pathways aren't responding correctly.
Treatment focuses on expanding blood volume through aggressive salt intake (often 8 to 10 grams daily, far more than typical dietary advice), increased fluid consumption (2 to 3 liters daily), and sometimes medications like fludrocortisone to help retain sodium and water. In stubborn cases, desmopressin may be used.
There's growing evidence that many cases of POTS involve autoimmune mechanisms. Research has found 89% of studied POTS patients had elevated antibodies against the alpha-1 adrenergic receptor, the receptor involved in blood vessel constriction. Additional studies have identified elevated ganglionic acetylcholine receptor antibodies in a smaller subset of pediatric POTS patients.
Autoimmune POTS often develops after viral infections, which may trigger the immune system to produce antibodies that cross-react with autonomic nerve receptors. Patients with this subtype frequently have other autoimmune conditions or a family history of autoimmunity.
Treatment may include standard POTS therapies plus approaches that address immune dysfunction. Some patients have responded to IVIG (intravenous immunoglobulin) or other immunomodulatory treatments, though these are generally reserved for severe cases that don't respond to other approaches.
While tachycardia is the defining feature, most POTS patients experience a constellation of symptoms that affect multiple body systems. This makes sense when you remember that the autonomic nervous system regulates virtually every organ.
Beyond the obvious rapid heart rate, patients commonly experience palpitations, chest discomfort, and fluctuations in blood pressure. Some people feel their heart pounding even when it's not particularly fast. Blood pressure can swing between too high and too low, sometimes within the same day.
Brain fog is one of the most disabling symptoms. Patient surveys have found 91% report forgetfulness, 89% report difficulty thinking, and 88% report difficulty focusing. Many describe it as trying to think through molasses or feeling like their brain is wrapped in cotton.
This isn't psychological — the cognitive symptoms correlate with reduced cerebral blood flow. When the brain isn't getting adequate blood supply, it can't function at full capacity. Dizziness, lightheadedness, headaches, and visual disturbances are also common.
The autonomic nervous system controls digestion, so GI problems are extremely common in POTS. Patients may experience nausea, bloating, constipation, diarrhea, or abdominal pain. Some develop gastroparesis (delayed stomach emptying). Food sensitivities often emerge or worsen.
Fatigue is nearly universal and often severe. Temperature regulation problems cause excessive sweating or inability to sweat normally. Exercise intolerance limits physical activity. Sleep disturbances compound the exhaustion. Some patients experience changes in skin color, hair loss, or issues with their extremities.
The breadth of symptoms is why POTS patients often see multiple specialists (cardiologist, neurologist, gastroenterologist, rheumatologist) without anyone connecting the dots. Each specialist sees their piece of the puzzle, but no one sees the whole picture.
POTS can develop from multiple triggers, and identifying the underlying cause (when possible) helps guide treatment.
A substantial share of POTS cases begin after a viral illness. This has become especially relevant since COVID-19, which has caused a dramatic increase in POTS cases linked to long COVID. Analysis of over 65 million US patient records showed a more than five-fold increase in new POTS diagnoses after the pandemic began.
Viruses can trigger POTS through direct damage to autonomic nerves, autoantibody production, persistent inflammation, or damage to blood vessel linings. Epstein-Barr virus, hepatitis C, and Lyme disease have also been associated with POTS onset.
This is where our clinical experience becomes particularly relevant. Brain injuries, including seemingly mild concussions, can trigger POTS by disrupting the brain regions that control autonomic function.
Research has found that 7 to 11% of concussion patients develop orthostatic tachycardia, and large pediatric POTS clinic populations consistently identify concussion as one of the top triggers, second only to infection. In one study of adolescents with post-concussion symptoms persisting three weeks or longer, 41% met criteria for POTS on tilt-table testing.
The mechanisms make sense anatomically. The brainstem, hypothalamus, and other structures controlling autonomic function can be affected by the forces involved in head injury. Diffuse axonal injury, inflammation, and disruption of normal neural pathways can all contribute to lasting autonomic dysfunction.
A case series documented eight patients who developed POTS after traumatic brain injury. All had been completely healthy beforehand. All developed orthostatic dizziness, fatigue, palpitations, and near-fainting episodes. Six of the eight also developed significant cognitive dysfunction.
At Cognitive FX, we frequently see patients whose POTS symptoms began after a head injury. Often, they've been told the concussion "should have healed by now" while continuing to struggle with autonomic symptoms that standard concussion management didn't address.
About 31% of POTS patients meet criteria for hypermobile Ehlers-Danlos Syndrome, and an additional 24% have generalized joint hypermobility without full hEDS criteria.
Studies of hEDS populations also show high rates of orthostatic intolerance.
The connection likely involves abnormal collagen in blood vessel walls, which allows them to stretch excessively and pool blood. There may also be shared mechanisms involving small fiber neuropathy and autonomic dysfunction.
About 42% of POTS patients show evidence of mast cell activation syndrome (MCAS), where mast cells release histamine and other chemicals inappropriately. Histamine causes blood vessels to dilate, contributing to blood pooling and hypotension. The combination of POTS, EDS, and MCAS has become recognized as a common triad.
Why patients struggle to get answers
Tap each card to learn more
Racing heart, dizziness, and brain fog start appearing, often after a viral illness or injury
Standard tests come back "normal." Patient is often told it's anxiety or stress
Cardiologist, neurologist, GI specialist each see their piece but not the full picture
Average of 4.9 years and 7 doctors before finding someone who recognizes POTS
A tilt table test confirms POTS. Treatment can finally begin.
The gold standard diagnostic test is the tilt table test. You lie flat on a table while your heart rate and blood pressure are monitored, then the table tilts to 60 or 70 degrees for at least 10 minutes.
POTS is confirmed when:
Some clinics use active standing tests or NASA lean tests as alternatives. A 24-hour Holter monitor can capture heart rate variability throughout daily activities. Additional tests may include blood volume measurement, catecholamine levels (to identify hyperadrenergic POTS), and autonomic reflex testing.
The average POTS patient waits years for diagnosis and sees multiple physicians before getting answers. Community surveys find that most patients are initially misdiagnosed with psychiatric conditions, and only a minority receive a correct diagnosis within the first year.
This delay happens partly because POTS symptoms overlap with many other conditions, partly because standard tests — routine blood work, EKGs, basic cardiac imaging — often come back normal, and partly because many physicians simply aren't familiar with the condition.
Treatment for POTS typically follows a stepwise approach, starting with lifestyle modifications and adding medications as needed.
Increased fluid and salt intake is usually the first recommendation. Most patients are advised to consume 2 to 3 liters of fluid and 8 to 10 grams of salt daily. This helps expand blood volume and is safe for most people, though those with kidney disease, heart failure, or certain other conditions need medical guidance.
Compression garments help prevent blood from pooling in the legs. Abdominal compression at around 40 mmHg is often more effective than leg compression alone. Waist-high compression is ideal if patients can tolerate it.
Physical counter-maneuvers like crossing the legs, squatting, or tensing muscles can help in the moment when symptoms flare.
Exercise reconditioning has strong evidence, though it needs to be approached carefully. The Levine Protocol (also called the Dallas Protocol) is the best-studied exercise program for POTS. It starts with recumbent exercises only (swimming, rowing, recumbent bike) for the first couple of months, then gradually introduces upright activity.
In studies of patients who completed the program, a substantial proportion no longer met diagnostic criteria for POTS at three months.
Midodrine is a vasoconstrictor that helps prevent blood pooling. Clinical evidence supports its benefit in reducing orthostatic symptoms.
Ivabradine slows the heart rate through a different mechanism than beta-blockers, which makes it particularly useful for hyperadrenergic POTS. In a randomized controlled trial, ivabradine improved heart rate and quality of life.
Beta-blockers like propranolol can help control tachycardia, though low doses work better than high doses (high doses can worsen fatigue).
Fludrocortisone helps the body retain sodium and expand blood volume, useful for hypovolemic presentations.
Pyridostigmine enhances parasympathetic activity and can help with both heart rate control and gastrointestinal symptoms.
These interventions help many patients, and some achieve excellent control of their symptoms. But a substantial number of people try multiple medications and lifestyle modifications and still struggle.
That's because most standard treatments target the downstream effects of POTS rather than the upstream dysfunction. Compression stockings counteract blood pooling. Salt increases blood volume. Beta-blockers slow the racing heart. But none of these address why the autonomic nervous system isn't regulating properly in the first place.
When POTS stems from brain dysfunction, whether from concussion, viral effects on the central nervous system, or other causes, the most effective treatment needs to address that brain dysfunction directly.
Emerging evidence supports treatment approaches that target the central autonomic network and promote neuroplasticity, the brain's ability to reorganize and heal.
A pilot study of an EEG-based neurotechnology called HIRREM in adolescents with POTS found improvements in heart rate variability and reduced temporal lobe electrical asymmetry after treatment. A subset of participants were able to reduce or discontinue their POTS medications.
Vagus nerve stimulation has also shown promise to help patients with combined epilepsy and POTS, where implanted VNS devices have been associated with resolution of orthostatic symptoms. The likely mechanism involves increasing parasympathetic activity to counter the sympathetic overdrive that characterizes many POTS cases.
Several strategies can help manage daily life with POTS and reduce flare-ups while seeking treatment.
At Cognitive FX, we've developed a 5-day intensive POTS program that treats the autonomic nervous system and brainstem centers driving the dysregulation, rather than treating the heart and blood vessels alone. The protocol didn't start as a POTS treatment. It emerged from years of treating post-concussion patients whose POTS symptoms consistently improved alongside their cognitive symptoms during neurological rehabilitation. We formalized those methods into a dedicated program.
The philosophy is different from standard POTS care. Rather than adjusting for a system that isn't regulating properly, we're recalibrating the regulator itself — the brainstem centers controlling heart rate and blood pressure, the vestibular sensors detecting position change, and the breathing mechanics affecting blood flow and brain oxygenation.
Day 1: Comprehensive evaluation. We assess orthostatic response, vestibular function, cranial nerve inputs, and breathing mechanics, then build a treatment plan calibrated to the specific pattern of dysregulation.
Days 2–5: Multi-modal treatment, 4–6 hours per day. Treatment includes:
Patients leave with a personalized home program calibrated to their specific dysregulation pattern, so the work continues after they go home.
Cost: $4,500, including the initial evaluation, all treatment sessions, and follow-up consultations. The program is not covered directly by most insurance plans, but we provide documentation to support out-of-network reimbursement claims, and payment plans are available.
The program is most likely to be a good fit for patients who have tried standard approaches — structured exercise training, salt and hydration loading, compression garments, and medications — without lasting improvement. Individual results vary."
Several strategies can help manage daily life with POTS and reduce flare-ups while seeking treatment.
Morning routine matters. Many patients feel worse in the morning after lying flat all night. Before getting out of bed, flex and point your feet repeatedly, tense your leg muscles, and sit up slowly before standing. Drinking a glass of water before you get up can help.
Stay cool. Heat worsens POTS symptoms for most patients by dilating blood vessels. Cool showers, air conditioning, and cooling vests can help during hot weather.
Eat smaller meals. Large meals divert blood to the digestive system and can worsen symptoms. Smaller, more frequent meals are usually better tolerated.
Identify your triggers. Alcohol, prolonged standing, dehydration, and certain medications can trigger symptom flares. Keeping a symptom diary can help identify your personal triggers.
Plan for good days and bad days. POTS symptoms often fluctuate. Having strategies for managing bad days (and not overextending on good days) helps maintain function over time.
If you suspect you have POTS, or if you've been diagnosed but aren't improving with standard treatment, here are some thoughts on finding the right care.
Get a proper diagnosis. When choosing a POTS clinic, look for a tilt table test or active standing test with clear documentation of heart rate response. Knowing which subtype(s) you have helps guide treatment.
Look for providers who understand the brain connection. The most effective treatment considers autonomic dysfunction as a problem of nervous system regulation, not just a cardiovascular issue.
Consider whether there's an underlying cause. If your symptoms started after a concussion, viral illness, or other identifiable trigger, treatment that addresses that underlying cause may be more effective than symptom management alone.
Don't give up. The average POTS patient waits years for diagnosis and tries multiple approaches before finding what works. Improvement is possible, especially when treatment addresses root causes rather than just managing symptoms.
POTS is a real, physiological condition that affects millions of people. It's not anxiety. It's not "all in your head." But ironically, it often is about the head, meaning the brain regions that control autonomic function.
Understanding POTS as a disorder of central autonomic regulation, not just peripheral blood flow, opens up new possibilities for treatment. When the brain's control centers for heart rate, blood pressure, and other automatic functions aren't working properly, the most effective solutions address that dysfunction directly.
If you've been struggling with POTS and haven't found relief with standard approaches, treatments that address brain function and promote neuroplasticity may help. For patients whose symptoms began after concussion or other identifiable triggers, this approach targets the dysfunction driving the condition rather than working around it.
If POTS is disrupting your life and standard treatment hasn't given you the relief you need, our 5-day neurologic POTS program may be a good next step. You can fill out a POTS intake form to see if you're a good fit, or call our clinic directly at 385-446-4158.
POTS (Postural Orthostatic Tachycardia Syndrome) is a condition where your heart rate increases by 30 or more beats per minute within 10 minutes of standing up. It's a form of dysautonomia, or dysfunction of the autonomic nervous system, which controls automatic body functions like heart rate and blood pressure. POTS affects 1-3 million Americans, predominantly women between the ages of 15 and 50.
The four main types of POTS are:
Neuropathic POTS (approximately 50% of cases) involves small nerve fiber damage that prevents blood vessels from constricting properly.
Hyperadrenergic POTS (30-60% of cases) features sympathetic nervous system overdrive with elevated norepinephrine levels.
Hypovolemic POTS (up to 70% of cases) involves low blood volume, averaging 13% below normal.
Autoimmune POTS (89% have elevated antibodies) is triggered by immune dysfunction, often following viral illness.
Many patients have overlapping types, which is why comprehensive evaluation matters.
Research increasingly shows POTS involves brain dysfunction, not just cardiovascular problems. Brain SPECT imaging in POTS patients with cognitive symptoms found 61% had reduced cerebral blood flow even while lying flat.
Neuroimaging reveals structural differences in brain regions controlling autonomic function, including the insular cortex, hypothalamus, and brainstem. This is why treatments targeting only the heart or blood vessels often fall short.
Yes, concussion is the second most common trigger for POTS after viral illness. Research shows 7-11% of concussion patients develop orthostatic tachycardia. Brain injuries can disrupt the brainstem, hypothalamus, and other structures controlling autonomic function, leading to lasting autonomic dysfunction including POTS. Many patients don't connect their symptoms to a prior head injury, especially if the concussion seemed mild.
The average POTS patient waits 4.9 to 6 years for diagnosis and sees 7 different physicians before getting answers. Studies show 83% are initially misdiagnosed with psychiatric conditions, and only 25% receive a correct diagnosis within the first year. This delay happens because POTS symptoms overlap with many conditions and standard tests often appear normal.
POTS treatment depends on the subtype and typically includes increased salt (8-10g daily) and fluid intake (2-3L daily), compression garments, and graduated exercise programs like the Levine Protocol. Medications may include midodrine, ivabradine, beta-blockers, or fludrocortisone depending on which type of POTS you have. For patients who don't respond to standard approaches, brain-based treatments targeting autonomic dysfunction directly show promise for achieving lasting improvement.

Alina Fong, Ph.D. is a clinical neuropsychologist and the Clinical Director and Co-Founder of Cognitive FX. She earned her Ph.D. in Clinical Neuropsychology with an emphasis in Neuroimaging from Brigham Young University, where she received the American Psychological Association Division 40 Graduate Student Research Award for her neuroimaging research. Dr. Fong has over 17 years of clinical experience treating traumatic brain injury, beginning with her work at the VA Salt Lake City Healthcare System and Utah Valley Regional Medical Center, where she directed the neurotrauma rehabilitation and sports concussion clinics. She developed the EPIC Treatment protocol and has personally overseen treatment for nearly 8,000 brain injury patients, including professional athletes from the NFL, NHL, and Olympics. She serves as Vice President of the Brain Injury Alliance of Utah, sits on the board of the United States Brain Injury Alliance, and advises PINK Concussions. Dr. Fong has authored peer-reviewed research on functional MRI and concussion treatment and has presented at over 60 medical conferences, including the Federal Interagency Conference on TBI and the American Medical Society for Sports Medicine.

If you’re living with POTS, you’ve probably wondered: Is this ever going to get better?

If you have POTS, you may know the pattern all too well: you stand up, and within seconds, a headache sets in. It eases off when you lie back down. It returns the next time you stand. Over and over,...

Hyperadrenergic POTS affects an estimated 30 to 60% of all POTS patients, yet most are never told which subtype they have. That matters because the hyperadrenergic form requires a fundamentally...

If you've been diagnosed with postural orthostatic tachycardia syndrome (POTS) or strongly suspect you have it, you already know how much it can affect your daily life. The dizziness when you stand,...

Finding effective care for postural orthostatic tachycardia syndrome (POTS) can be more challenging than you would expect. Most healthcare providers approach POTS as a cardiovascular issue — focusing...
